 EN
Researchers from Deutsches Diabetes-Zentrum, together with Universitätsklinikum Düsseldorf and Universitätsklinikum Tübingen, have identified three distinct subgroups of adult-onset type 1 diabetes. Published in a major medical analysis based on data from the German Diabetes Study, this discovery reveals that adult-onset type 1 diabetes is far more heterogeneous than previously understood. Particularly notable is a mixed subgroup that combines features of both classic type 1 and type 2 diabetes, caught at a significantly earlier stage of the autoimmune process. For patients traveling to Germany for specialized endocrine evaluation, these insights provide a crucial foundation for earlier diagnostic precision, tailored insulin strategies, and targeted preservation of remaining pancreatic beta cells.
Understanding Type 1 Diabetes Onset in Adulthood
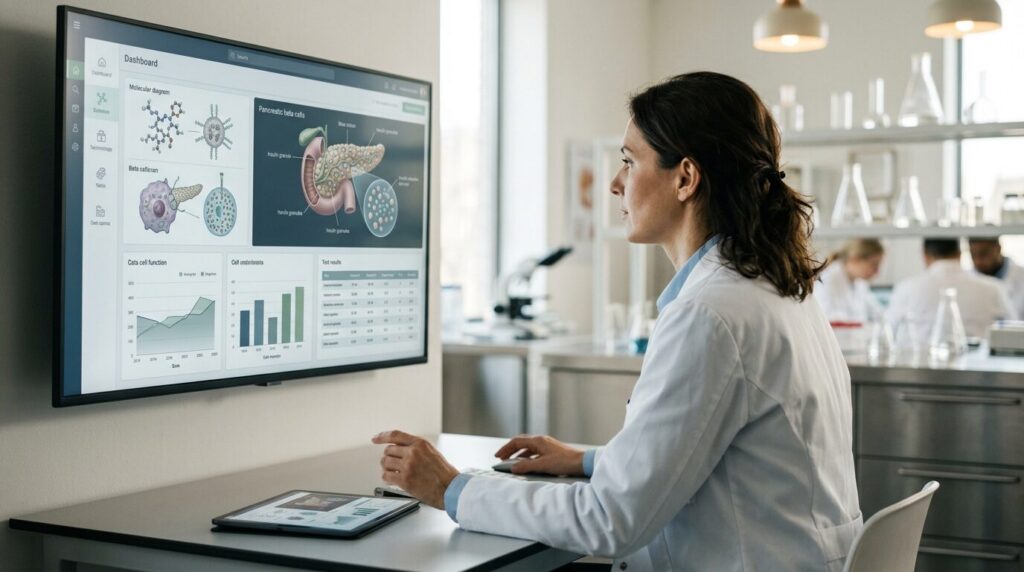
Type 1 diabetes is traditionally understood as an autoimmune condition that manifests predominantly during childhood or adolescence. In this disease, the body’s immune system mistakenly attacks and destroys the insulin-producing beta cells situated within the islets of Langerhans in the pancreas. Without sufficient insulin, glucose cannot enter cells to provide energy, leading to elevated blood sugar levels and long-term metabolic disruption. However, clinical experience has increasingly demonstrated that type 1 diabetes can also develop much later in life. When diabetes appears in adults, it is frequently misidentified as type 2 diabetes because adult patients often present with overlapping clinical features, such as overweight or mild insulin resistance.
The diagnostic distinction between different diabetes types in adults remains one of the most complex challenges in modern endocrinology. Unlike children, in whom pancreatic beta cell loss often occurs rapidly and severely, adults frequently experience a more gradual decline in endogenous insulin secretion. This residual capacity to produce insulin can mask the underlying autoimmune destructive process for months or even years. Consequently, many adult patients are initially treated with lifestyle modifications or oral blood glucose-lowering medications typically reserved for type 2 diabetes. While these interventions may offer temporary glycemic control, they fail to address the fundamental autoimmune destruction taking place inside the pancreas.
Accurate and timely diagnosis is essential for preventing acute metabolic crises such as diabetic ketoacidosis and minimizing long-term microvascular and macrovascular complications. In comprehensive German medical centers, state-of-the-art diagnostic protocols routinely employ highly specific laboratory evaluations to clarify ambiguous diabetes presentations. By measuring key autoimmune markers alongside metabolic indicators, specialized endocrinologists can evaluate both the autoimmune activity and the remaining functional capacity of the pancreas. Understanding the full spectrum of adult-onset diabetes enables clinicians to optimize therapeutic strategies early, ensuring that patients receive the exact level of metabolic support and monitoring required for their specific disease profile.
Three Distinct Subgroups Identified by German Researchers
To systematically clarify the diversity of adult-onset type 1 diabetes, researchers analyzed comprehensive clinical data from 600 adult participants in the German Diabetes Study, known as GDS. All participants had received a diagnosis of diabetes within the preceding twelve months. Using an advanced statistical clustering approach based on five key laboratory parameters, including specific autoantibodies and C-peptide levels which directly reflect endogenous insulin production, the scientific team categorized the patients into three distinct subgroups. To confirm the validity of these findings, the researchers applied the same analytical framework to a second, independent dataset consisting of 483 adults with type 1 diabetes, which successfully demonstrated a nearly identical subgroup structure.
The analysis revealed clear differences in clinical characteristics and metabolic profiles across the three identified patient groups. The first group represented classic type 1 diabetes, where patients had an average age of 34 years, were generally lean, exhibited high insulin sensitivity, and produced minimal amounts of endogenous insulin at the time of diagnosis. The second group, designated as mixed type 1 diabetes, comprised older individuals with an average age of 41 years who had higher body weight, reduced insulin sensitivity, and significantly higher levels of remaining endogenous insulin. Notably, both classic and mixed subgroups tested positive for GAD autoantibodies, confirming the presence of an active pancreatic autoimmune process in both cohorts.
Crucially, the study established that classic and mixed type 1 diabetes share the exact same genetic risk profile and autoimmune markers, indicating that they represent different stages of the same underlying disease process rather than separate pathological entities. Dr. Katsiaryna Prystupa, a scientist at Deutsches Diabetes-Zentrum and physician at the Clinic for Endocrinology and Diabetology at Universitätsklinikum Düsseldorf, explained this phenomenon using the analogy of a marathon race. While a patient with classic type 1 diabetes reaches diagnosis near kilometer 40 with severe beta cell depletion, a patient with mixed type 1 diabetes is diagnosed at kilometer 20, with substantial functional cell mass still intact. Mathematically, this corresponds to a temporal difference of approximately six years in disease progression.
Clinical Implications and Future Personalised Treatments

The discovery of these distinct subgroups carries profound implications for clinical practice and diagnostic approaches in adult endocrinology. Prof. Michael Roden, scientific director and board spokesman of Deutsches Diabetes-Zentrum as well as director of the Clinic for Endocrinology and Diabetology at Universitätsklinikum Düsseldorf, emphasized that clinicians must account for this clinical diversity when evaluating adults with new-onset diabetes. Identifying the mixed subtype at an earlier functional stage opens up an important therapeutic window. During this phase, emerging disease-modifying therapies and novel immunomodulatory strategies could potentially be deployed to protect and preserve the remaining insulin-producing beta cells before total destruction occurs.
Beyond refining diagnostic categories, the research team investigated how these distinct subgroups correlate with long-term diabetic complications. Prof. Andreas Fritsche, head of the Department of Prevention and Care of Diabetes Mellitus at Universitätsklinikum Tübingen, noted that after adjusting for confounding factors such as age, sex, body weight, blood pressure, and smoking habits, patients with mixed type 1 diabetes showed an increased frequency of retinal microvascular damage, known as diabetic retinopathy. Although these findings require further confirmation through larger longitudinal clinical studies, they underscore the vital importance of specialized, early screening for ocular and vascular health in patients diagnosed with mixed type 1 diabetes.
The research also highlights critical considerations for the third subgroup identified in the study, which consists of patients presenting without detectable autoantibodies. Prof. Robert Wagner, head of the Clinical Study Center at Deutsches Diabetes-Zentrum and senior physician at Universitätsklinikum Düsseldorf, stressed that individuals in this category face a significant risk of misdiagnosis. Without autoantibodies, these patients are frequently classified as having type 2 diabetes, which can lead to inappropriate treatment delays in initiating necessary insulin therapy. For international patients seeking advanced care in Germany, thorough diagnostic evaluation—including monitoring C-peptide and metabolic dynamics—ensures precise subgroup categorization, optimized therapeutic regimens, and comprehensive long-term complication screening.
Source: Deutsches Diabetes-Zentrum