EN
In Germany, bladder cancer treatment depends on depth: superficial tumours are removed through the urethra, while deeper ones often mean removing the bladder. Bladder cancer often announces itself quietly: blood appears in the urine without pain and disappears again, and it is easily put down to an infection. A course of antibiotics follows, the symptom passes and the cause remains.
People often come to the question of treatment in Germany already diagnosed but with two doubts: how deeply the tumour has grown and whether the bladder can be kept. Bladder cancer treatment in Germany is built around exactly that question.
One question decides everything
The key question with a bladder tumour is whether it has grown into the muscle layer of the wall or is still superficial. Literally everything depends on that: the extent of the treatment and whether the organ can be preserved. Most tumours are superficial at the time they are found, which is good news — but that can be confirmed only by accurate assessment, not from symptoms.
Ta and T1 are superficial T stages, T2 and above reach the muscle. The grade (G) shows how abnormal the cells are; high-grade tumours recur and progress more often. Carcinoma in situ is a flat, aggressive form that does not protrude and is easily missed.
Location matters too: dome, side wall or bladder neck. A bladder-neck tumour is planned separately: the sphincter and, in men, the prostate lie close by, affecting the operation and continence. The Krebsinformationsdienst of the German Cancer Research Center explains the stages in German.
How the diagnosis is confirmed: cystoscopy and TURBT
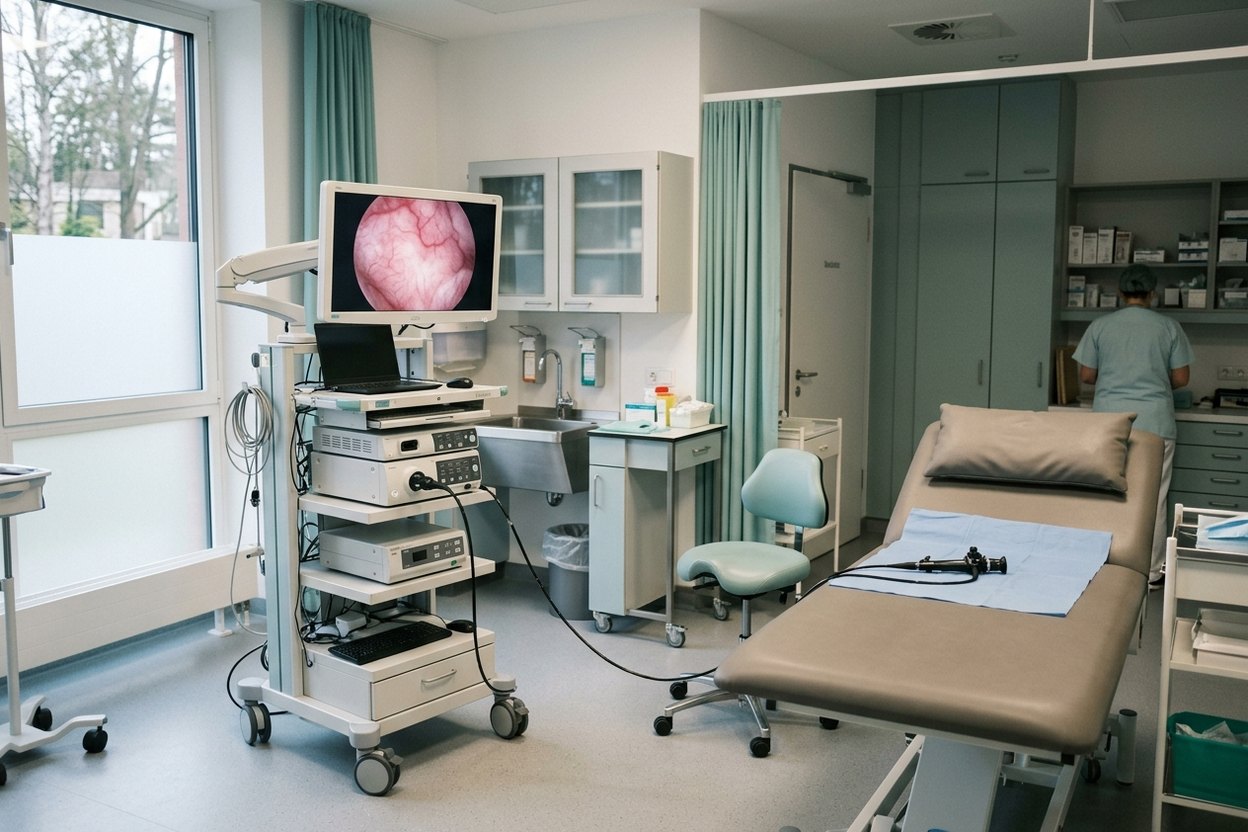
Diagnosis takes two steps: a look inside, then removal for analysis. It starts simply — a urine test, including cytology, in which the urine is checked for tumour cells, and ultrasound. The main method is cystoscopy: a thin instrument with a camera is passed through the urethra and the wall of the bladder is examined from inside. German hospitals often use fluorescence cystoscopy: a substance put into the bladder makes tumour tissue glow under a special light, showing even small, flat lesions that ordinary light might miss.
The diagnosis and the stage are established by transurethral resection (TURBT): the tumour is removed through the urethra and examined by a pathologist. It is the pathologist who determines the type of tumour, its grade and — most important — whether it has penetrated the muscle layer. CT or MRI is added where the spread has to be assessed. Thus TURBT is at once diagnosis and the first stage of treatment. If the tumour is aggressive or the sample lacks muscle, TURBT is repeated a few weeks later: cells often remain, and the stage may be underestimated.
In Germany, bladder cancer is treated in uro-oncology centres. Partners include the certified centres of the urology departments at University Hospital Essen with the West German Cancer Centre (Prof. Boris Hadaschik) and at University Hospital Tübingen (Prof. Igor Tsaur), Marienkrankenhaus Hamburg (Prof. Michael Rink) and the uro-oncology centre at München Klinik Bogenhausen. See also bladder cancer diagnostics.
Treatment of a superficial tumour
For a superficial tumour, bladder cancer treatment in Germany usually means TURBT followed by local treatment placed directly into the bladder (instillations). A chemotherapy solution or BCG vaccine, which triggers a local immune response against the remaining cells, is instilled into the bladder. That approach is gentle: the drug acts inside the bladder and barely touches the rest of the body.
Follow-up is then done regularly by cystoscopy — with this tumour it matters to notice any return in time. The doctor sets the instillation schedule by risk: one dose after TURBT, or a course plus maintenance for months, with BCG often for years. Burning and frequent urination are common; BCG may cause a flu-like reaction. If BCG fails, German guidelines advise considering bladder removal; for carcinoma in situ, new medicines were recently approved in the EU.
If the tumour has grown into the muscle layer
If the tumour has grown into the muscle layer, the approach is more serious: one of the main options is removal of the bladder (cystectomy) with a new route for the urine. In some cases a reservoir replacing the bladder is formed from a section of bowel: joined to the urethra, it is emptied naturally but by the clock, as there is no urge. A pouch is emptied by catheter through the navel; a conduit drains urine via a piece of bowel into a bag on the abdomen. Each has its own cost in daily life.
As an alternative, a bladder-sparing approach is considered for selected patients — TURBT combined with chemotherapy and radiotherapy. Drug therapy, including immunotherapy chosen by the features of the tumour, is often used before and after the operation. What is suitable is decided by the tumour board — urologist, oncologist and radiation oncologist together. See also bladder cancer surgery and bladder cancer immunotherapy.
Most patients leave hospital two to three weeks after cystectomy, usually for rehabilitation. The new reservoir starts small and is trained: capacity is built up gradually and the pelvic floor strengthened. Night-time leakage is common in the first months, while the sphincter is still weak; exercises and an alarm clock to empty the reservoir help.
Second opinion and follow-up
Between “remove the bladder” and “try to preserve it” lies a difficult decision, and it is worth weighing with a doctor who manages such cases often. A German specialist reviews the TURBT result and the histology, the cystoscopy findings and the images, and says whether they agree with the assessment of the depth of invasion and with the plan. Sometimes that is what determines whether a person keeps their own bladder — the purpose of a second opinion from a German doctor. Stories and forums help prepare for the talk with the doctor but do not replace a review of one’s own case; see how to read reviews of cancer treatment in Germany.
Follow-up lasts years: after a superficial tumour, cystoscopy and urine cytology, first every few months, later less often; after cystectomy, CT, blood and urine tests and ultrasound, which also check the kidneys. The schedule comes with the discharge letter.
Frequently asked questions
What are the newest treatments for bladder cancer?
Immunotherapy, antibody-drug conjugates and bladder-sparing treatment. In the EU, immunotherapy is now also used before and after bladder removal. The antibody-drug conjugate enfortumab vedotin carries its drug into cancer cells. For carcinoma in situ unresponsive to BCG, new bladder instillations are approved. A uro-oncologist decides what fits.
Can the bladder be preserved?
Yes, with a superficial tumour the bladder is usually kept: the tumour is removed through the urethra, then instillations follow. With muscle invasion the bladder is more often removed, but selected patients can have TURBT with chemotherapy and radiotherapy; if tumour remains, the bladder is removed.
Is bladder cancer curable?
Often, yes; the chances depend mainly on the stage. A superficial tumour usually responds well but often recurs. Without metastases, treatment aims at cure even when the muscle is involved. If the disease has spread, treatment holds it back and eases symptoms.
How AlenMed arranges treatment in Germany
AlenMed guides the patient from the first documents to discharge: we read the reports and histology, choose a uro-oncology centre by depth of invasion and whether the bladder may be kept, and obtain the clinic’s official cost estimate (Kostenvoranschlag; see bladder cancer treatment costs). We handle visa papers, meet the patient and provide a medical interpreter for appointments and the ward. Our office is in Munich; partner clinics span Germany.
This material is for information only, does not replace a consultation with a doctor and is not a public offer. Whether treatment is possible, what it will involve and what it will achieve can be determined only after an examination at the clinic in person.
News on this topic
Charité treats first beta-thalassemia patient with CRISPR
At Berlin Charité, a 19-year-old beta-thalassemia patient became the first in Germany to receive the newly approved CRISPR gene therapy Exagamglogene Autotemcel.
Real-World Breast Cancer Study Confirms High Five-Year Survival Rates in Germany
A landmark study of over 43,000 German patients reveals a five-year invasive disease-free survival rate of 82.9 percent in early hormone receptor-positive breast cancer.
FDA Approves Jülich Diagnostic Radiotracer FET for Brain Tumor Imaging
The FDA approves the diagnostic radiotracer FET (Pixclara®) for evaluating brain gliomas, highlighting decades of neuro-oncology research at Forschungszentrum Jülich.