EN
Stomach cancer treatment in Germany starts by establishing precisely what kind of tumour it is and how far it has spread. At first the disease passes for everyday complaints, such as heaviness after meals, heartburn, feeling full after a few bites or weakness, easily blamed on a “nervous stomach” until weight loss or traces of blood appear. Many patients arrive with a diagnosis from home and questions about the stage and the extent of surgery.
This page covers what decides the plan, early tumours removed through the endoscope, surgery with chemotherapy, advanced disease, hospitals and arrangements. Non-cancer complaints such as gastritis have a separate page.
What decides the treatment plan
The plan depends first on the stage: how deep the tumour has grown into the stomach wall and whether lymph nodes or other organs are involved. Location matters too: tumours at the junction with the oesophagus are planned partly like oesophageal cancer.
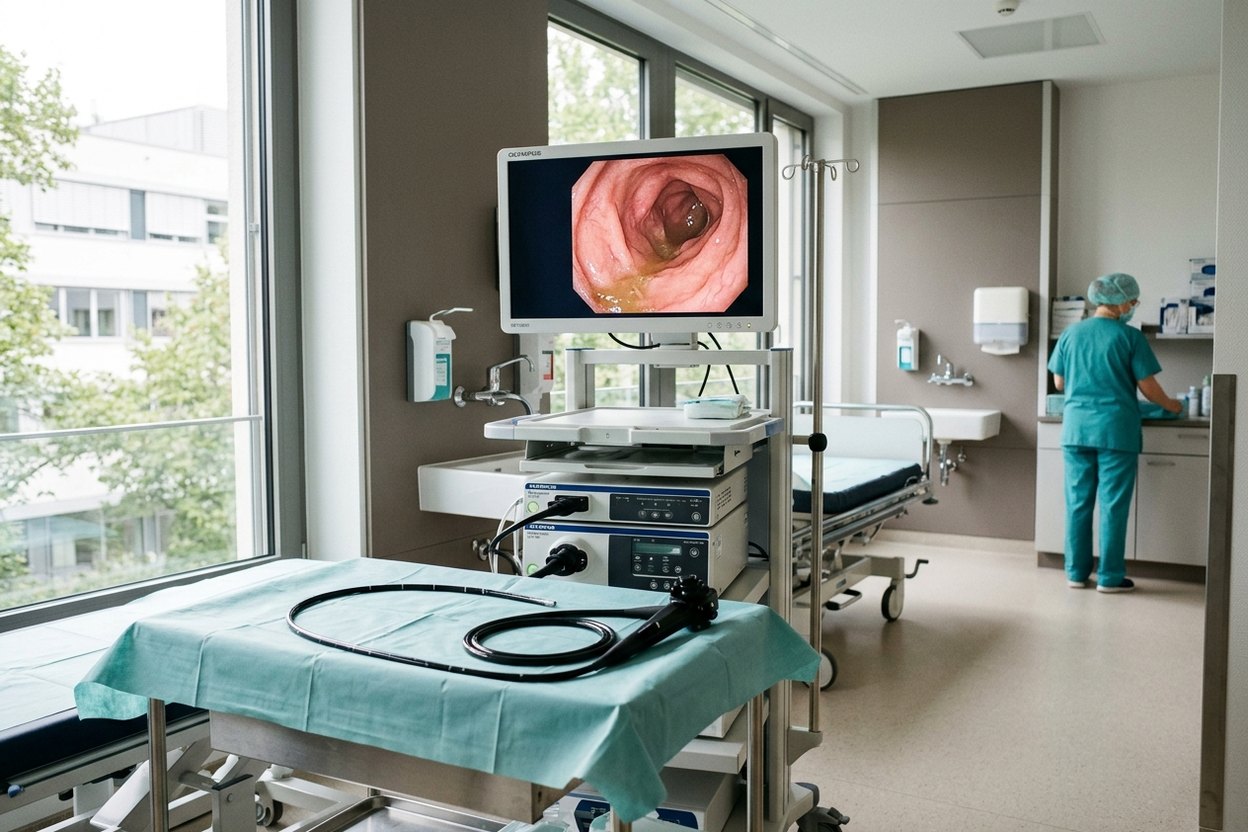
Gastroscopy with biopsy gives the definitive answer: a pathologist examines tissue samples taken from inside the stomach. Endoscopic ultrasound, in which a probe on the tip of the endoscope shows the layers of the wall, measures the depth and checks nearby lymph nodes. CT of the chest and abdomen looks for spread; PET is used only for specific reasons. For deeper tumours a diagnostic laparoscopy is recommended before chemotherapy, since small deposits on the abdominal lining often escape CT. See digestive system diagnostics in Germany for details.
The tissue is also tested for HER2, microsatellite instability (a defect in the cell’s DNA repair system) and PD-L1: these features decide whether targeted drugs or immunotherapy will be considered. The plan is set by a tumour board (Tumorboard) of surgeon, medical oncologist, gastroenterologist and pathologist.
Early stomach cancer: removal through the endoscope
A small early tumour confined to the inner lining can sometimes be cut out during an endoscopy without opening the abdomen, and the stomach is kept. In this endoscopic submucosal dissection, fluid injected beneath the tumour lifts it, and it is removed in one piece with the layer beneath. The procedure is done in hospital by endoscopists experienced in the technique.
The specimen then goes to the pathologist, because only the microscope shows whether the tumour reached deeper than expected and whether the edges are clear. If it did, or unfavourable features are found, the tumour board recommends surgery with removal of the lymph nodes. After complete removal, regular check endoscopies help to spot a recurrence or a new tumour early.
Surgery and chemotherapy around it
When endoscopic removal is not enough, surgery is the basis: part or all of the stomach is removed with the surrounding lymph nodes, depending mainly on the tumour’s location and type. With a tumour in the lower stomach the upper part can often be kept; higher up, the whole stomach is usually removed. Experienced centres also operate laparoscopically or with a surgical robot. For early tumours laparoscopic surgery is equivalent to open surgery, for advanced ones it is still under study, so the surgeon decides case by case.
For locally advanced tumours, perioperative chemotherapy is the standard in Germany: it starts before the operation and continues after it. Courses before surgery aim to shrink the tumour, those after it to lower the risk of recurrence, and continuing depends on response and tolerance. This is set out in the German S3 guideline on gastric cancer. Radiotherapy is not a main treatment for cancer of the stomach itself. For tumours at the junction with the oesophagus, radiotherapy with chemotherapy before surgery is an alternative to perioperative chemotherapy, chosen by the tumour board.
Life after gastrectomy needs adjustment, which starts in hospital: small, frequent meals eaten slowly, with a dietitian’s advice before and after the operation. Without the stomach, vitamin B12 is no longer absorbed from food, so it is given for life, usually by injection, less often as high-dose tablets. Weight is monitored, especially in the first year, and rehabilitation in a specialised clinic is possible after discharge.
When the cancer has spread
When the cancer has spread, treatment rests on drugs, with the aim of holding back the disease and keeping quality of life. Combination chemotherapy usually comes first. For HER2-positive tumours a targeted antibody is added, and for suitable tumour features immunotherapy, described under cancer immunotherapy.
Supportive care is part of the plan: nutrition, through a tube or drip if needed; a stent, a thin mesh tube that reopens the passage when the tumour blocks food; radiotherapy to stop bleeding or ease pain; and pain relief. Costs are explained on the stomach cancer treatment costs page.
Whether the disease can still be treated at this stage, what treatment can achieve, when chemotherapy inside the abdomen (HIPEC, PIPAC) is considered for peritoneal deposits and when surgery is done is the subject of the article on stage 4 stomach cancer. In Germany these methods are offered by selected centres, PIPAC only within trials.
Where stomach cancer is treated in Germany
Stomach cancer is treated at hospitals with specialised centres, and the German guideline advises a certified stomach cancer centre (Magenkrebszentrum), audited by the German Cancer Society: it must perform a minimum number of operations a year and discuss practically every patient at a tumour board before treatment. At Krankenhaus Nordwest in Frankfurt, Prof. Thilo Welsch heads general, visceral and tumour surgery, focusing on minimally invasive oesophageal and stomach surgery and robotic surgery. At Helios Klinikum Erfurt, stomach surgery belongs to the visceral oncology centre, which brings together bowel, stomach and pancreatic cancer centres, and robotic operations are performed there too.
At München Klinik Bogenhausen, Dr Martin Fuchs heads gastroenterology; he treats early cancers of the oesophagus and stomach endoscopically and directs drug therapy for digestive cancers. The hospital is chosen by stage and by the treatment needed, whether endoscopy, surgery or drugs, not by the name of the city.
Frequently asked questions
How is stomach cancer treated today?
Stomach cancer is treated according to its stage. Early tumours confined to the inner lining are removed endoscopically. Locally advanced tumours receive chemotherapy before and after an operation that removes part or all of the stomach. When the disease has spread, chemotherapy is the basis, combined with a targeted drug or immunotherapy if the tumour’s features allow.
How quickly can stomach cancer treatment start in Germany?
Treatment can start once the hospital has reviewed your documents and set a date, so the timing depends on which documents and tests already exist. Doctors first study the discharge letters, images and histology. Recent good-quality tests are usually not repeated, while slides and tissue blocks are often re-examined: part of the plan, not a delay.
Does the whole stomach have to be removed?
No, not always. A small early tumour confined to the inner lining can sometimes be removed endoscopically. With a tumour in the lower stomach, often only part of the organ is removed if a safe margin is possible. The whole stomach is usually removed when the tumour sits higher up or spreads diffusely through the wall. The tumour board sets the final extent.
How AlenMed arranges stomach cancer treatment
AlenMed starts with the documents: gastroscopy and histology reports, CT and PET discs, and the paraffin tissue blocks if tumour features still need testing. We translate them and arrange a review at centres across Germany; it sometimes changes the extent of the planned operation, which is what a second opinion in Germany is for.
We prepare the visa invitation and arrange an interpreter at appointments and accommodation near the hospital. You go home with a written plan for follow-up and nutrition. AlenMed’s office is in Munich; partner hospitals are all over Germany.
This material is for information only and is not an offer. The treatment plan is set by the doctor at an in-person consultation.
News on this topic
Charité treats first beta-thalassemia patient with CRISPR
At Berlin Charité, a 19-year-old beta-thalassemia patient became the first in Germany to receive the newly approved CRISPR gene therapy Exagamglogene Autotemcel.
Real-World Breast Cancer Study Confirms High Five-Year Survival Rates in Germany
A landmark study of over 43,000 German patients reveals a five-year invasive disease-free survival rate of 82.9 percent in early hormone receptor-positive breast cancer.
FDA Approves Jülich Diagnostic Radiotracer FET for Brain Tumor Imaging
The FDA approves the diagnostic radiotracer FET (Pixclara®) for evaluating brain gliomas, highlighting decades of neuro-oncology research at Forschungszentrum Jülich.