EN

A patient with a cancer diagnosis is not shopping for a country but looking for certainty: an exact diagnosis and a plan they can trust. Cancer treatment in Germany starts precisely there, with establishing what the disease is and what should happen next. By the time treatment abroad comes up, time has usually been lost and contradictory reports have piled up, so people come not for “some treatment” but for a clear picture and a plan in which every step is explained.
This page explains how oncology in Germany is organised: who decides on treatment, which tests come first, which methods are used, where treatment takes place and what the bill is made of. Each tumour type has its own page in the navigation below this text.
Why patients travel to Germany for oncology
Patients travel to Germany for oncology because treatment here is built around specialists working together, and in oncology the outcome depends most on how well they do. That is why the tumour board sits at the centre of the German system. Germany has fourteen top-level cancer centres (Onkologische Spitzenzentren), selected and funded by the charity Deutsche Krebshilfe (German Cancer Aid); one of them is in Munich, run jointly by the LMU and TUM university hospitals.
What makes such a centre different from a merely good hospital is how the decision is made. Every complex case is reviewed by a tumour board: an oncologist, a surgeon, a radiologist, a radiation oncologist and a pathologist look at the scans, biopsy results and history together and agree on a common approach. This reduces the risk of something being missed or of treatment being given out of habit.
Oncology treatment in Germany follows the clinical guidelines of the German medical societies, the strictest of which are the S3 guidelines (S3-Leitlinien): they rest on a systematic review of the research and are agreed by representatives of the relevant societies, so each step is reasoned and reproducible rather than dependent on one doctor’s habits. The guidelines are public and can be found in the AWMF guideline register. There is no honest ranking of countries or cities: it makes sense to compare centres treating your tumour type, and how that choice looks across the continent is covered in our article on cancer treatment in Europe.
Cancer treatment in Germany for foreigners: the route step by step
The route starts before the trip, with records on which a German specialist gives a remote opinion. Most people seeking treatment in Germany for cancer arrive with a diagnosis made at home, and the records behind it are what the specialist needs first: discharge reports, the pathology report (plus the slides or tissue blocks if a biopsy has been done), CT, MRI and PET scans on disc, recent blood tests and a list of the treatment already given. From these the doctor says whether the diagnosis is clear, what is missing and whether the trip makes sense; this is how a second opinion from a German doctor works.
Next come arrival and examination on site, and here the logic of a German doctor matters: treatment starts with verifying the diagnosis, not with executing it. Some tests are added or repeated and a pathologist re-examines the tumour tissue, and this not infrequently refines or changes what was established at home — the whole plan changes with it. Once the results are in, the tumour board reviews the case and draws up the plan: what comes first, what follows and how the response will be judged.
Then treatment begins — surgery, radiotherapy, drug therapy or a combination — and after each stage the doctors check how the tumour has responded. The patient leaves with a discharge report in hand: the diagnosis, what was done and a follow-up plan for home, with the tests and scans due and when. Check-up results can be sent to the treating doctor in Germany, who will say whether anything needs to change. Recovery after surgery, chemotherapy or radiotherapy is a stage of its own, covered on the page on oncological rehabilitation in Germany.
Cancer treatment in Germany for foreigners also has a practical side: an invitation for the medical visa, a medical interpreter at consultations, records in translation and a length of stay that follows the plan, since a round of tests takes less time than an operation or a course of radiotherapy. How quickly treatment can start depends on how complete the records are, on the department’s reply, on whether tests must be repeated on site and on the visa timeline. If the patient’s condition is serious and a regular flight is impossible, a flight with medical escort is arranged separately.
Diagnosis comes first
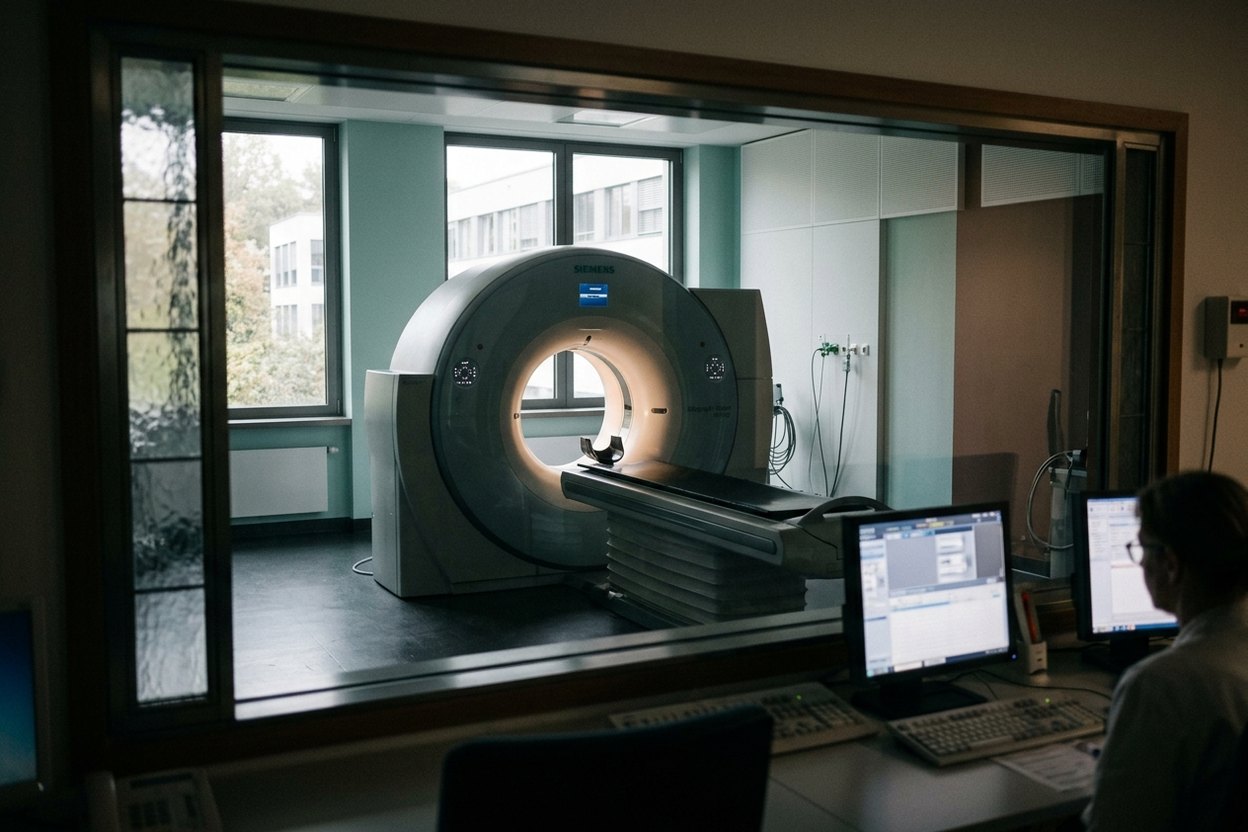
Diagnosis comes first, and the tests are chosen for the case: the doctor orders what the treatment decision needs and nothing for show — blood work, ultrasound, CT and MRI, endoscopy and, where needed, a biopsy with histology, the examination of tissue under a microscope. The aim is a complete picture: where the tumour is, how large it is and whether lymph nodes or other organs are involved.
PET-CT stands apart. It combines positron emission tomography with computed tomography: a weakly radioactive glucose-based substance is injected first, and because tumour cells usually consume sugar more actively than healthy ones, they stand out on the scan. So PET-CT shows tissue activity, not only the shape of an organ, and helps to see whether the tumour has spread beyond its original border.
Pathology, the examination of the tumour tissue itself, plays the key role. Treatment increasingly rests on the tumour’s molecular profile, which shows whether it has features that targeted or immune therapy acts on: diagnosis now answers not only “what is this” but also “what treats this in your case”. Why a targeted drug works only when its target is present is explained clearly by the Cancer Information Service of the German Cancer Research Center (in German).
Methods: surgery, radiotherapy, drug therapy
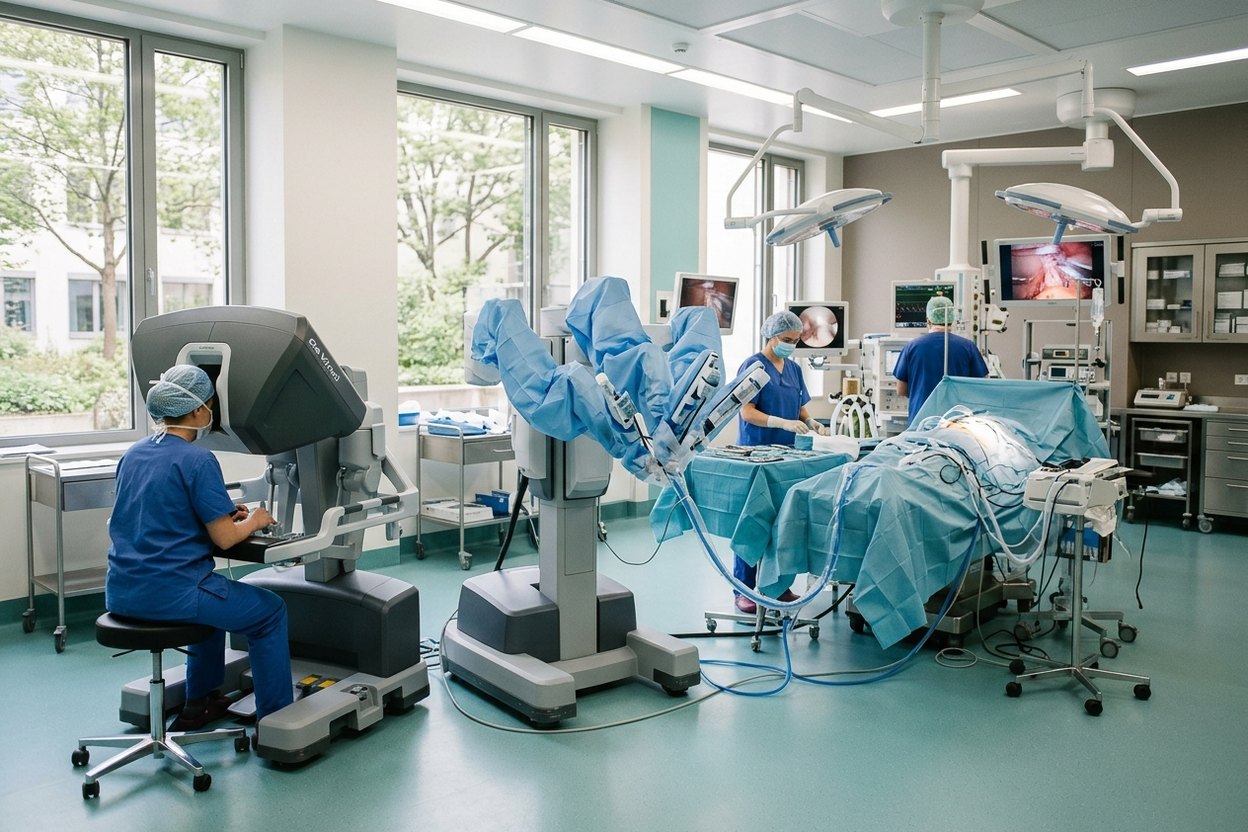
Treatment for cancer in Germany rests on three pillars — surgery, radiotherapy and drug therapy — and most often they are combined. Surgery is discussed when the tumour can be removed; many operations are done through small incisions, some with a robot-assisted system that the surgeon guides from a console. Sometimes the operation comes first; sometimes the tumour is shrunk beforehand with chemotherapy or radiotherapy.
Radiotherapy is discussed as treatment on its own, alongside surgery, or to relieve pain and other symptoms; modern machines shape the dose to the tumour and spare the tissue around it. Proton therapy uses charged particles that release most of their energy deep inside the tumour itself and touch less tissue on the way; it suits only certain tumours, and few facilities in Germany offer it.
Chemotherapy acts on rapidly dividing cells throughout the body. It is the sole standard treatment only in a few cancers; more often it is given before surgery to shrink the tumour or after it to destroy the cancer cells that remain. The regimen is chosen from the guidelines for the specific tumour type and stage.
Targeted drugs act on specific features of tumour cells, so they are prescribed only when such a target has been found by molecular testing. Immunotherapy helps the body’s own immune system recognise and attack the tumour; it is discussed above all in advanced disease and in the cancers for which the drugs are approved.
Several high-precision and newer methods complement this. Radiosurgery (CyberKnife, Gamma Knife) aims a high dose at a small, well-defined lesion, most often a metastasis in the brain. For liver metastases, local treatment is discussed: radioembolisation (SIRT) delivers radioactive microparticles through the blood vessels, chemoembolisation injects a drug into the tumour’s vessels and closes them off, and thermal ablation destroys a lesion with heat through a thin probe. Radionuclide therapy, such as PSMA therapy in advanced prostate cancer, brings radiation directly to the tumour cells. CAR-T cell therapy in certain leukaemias and lymphomas uses the patient’s own immune cells reprogrammed in a laboratory, and haematopoietic stem cell transplantation is used in blood cancers. When the peritoneum is affected to a limited extent, surgery may be combined with heated intraperitoneal chemotherapy (HIPEC). None of these replaces standard treatment or suits everyone: the tumour board decides who they are for. There is no single schedule “against cancer”, and a good clinic never claims one. To the question about the “best cancer treatment in Germany” there is an honest answer: it is the one the tumour board chooses for a specific tumour. Some private clinics sell foreign patients courses outside the German guidelines as a substitute for standard treatment; before paying, ask which guideline or study the method rests on and whether a tumour board has approved it.
Where cancer is treated in Germany: certified centres
Cancer is treated in many German hospitals, but a specialised centre stands out by its certificate from the German Cancer Society (Deutsche Krebsgesellschaft, DKG). It is awarded to organ cancer centres — for breast, bowel, prostate, lung and other cancers — and to oncology centres treating several tumour types under one roof. Certification means the department is audited from outside every year: experts check how many such patients it treats, how its specialists work together, including in the tumour board, and how closely treatment follows the guidelines. Above these stand the top-level centres mentioned earlier. How audits work and how to find a certified centre is explained by the DKG certification system (in German).
A few examples. The LMU Comprehensive Cancer Center in Munich brings together certified organ cancer centres for breast, bowel, prostate, lung, neuro-oncology and others. Krankenhaus Nordwest in Frankfurt is part of the University Cancer Center Frankfurt–Marburg (UCT), certified by Deutsche Krebshilfe. The university hospitals Charité in Berlin, Heidelberg and Freiburg are hospitals of maximum care with their own cancer centres: the Charité Comprehensive Cancer Center, the National Center for Tumor Diseases (NCT) Heidelberg and the Tumorzentrum Freiburg – CCCF. When choosing, look not at the fame of a name but at a certificate for your tumour type, the number of such cases treated a year and a tumour board that really works; a doctor is chosen the same way, by tumour type rather than magazine rankings. The full review is on the page Cancer hospitals in Germany.
What the treatment costs
There is no single price for cancer treatment: the sum follows the diagnosis and stage, the volume of tests needed on site and the chosen tactic — surgery, radiotherapy, drug therapy or a combination. Two patients with the same diagnosis can therefore receive quite different bills.
The exact sum comes from a cost estimate, the Kostenvoranschlag: the clinic calculates it from the medical report and issues it in the patient’s name. The estimate lists the items separately, and payment goes directly to the clinic. If the plan changes during treatment, the clinic recalculates the cost and agrees the new estimate with the patient.
Usually counted separately are the examination, the inpatient stay, drug therapy, accommodation outside the hospital and interpreter services. The German state does not pay for the treatment of foreign patients who travel for it; the options — insurance, charitable foundations, quotas in the patient’s own country — are covered on the page State-funded treatment in Germany. Figures published online are a guide, not a price list, as they cannot reflect your diagnosis or the tests you need; reference prices for the main treatments are on the page Cancer treatment costs.
Frequently asked questions
How is cancer treated in Germany?
Cancer in Germany is treated step by step: the diagnosis is verified first, then a tumour board reviews the case, and only then does treatment begin. The board chooses surgery, radiotherapy, drug therapy or a combination according to the German clinical guidelines, the S3-Leitlinien. After discharge the patient receives a follow-up plan, and the treating doctor stays in touch to help interpret the results of check-ups.
Why repeat tests if the diagnosis was already made at home?
Only what the treatment decision needs is repeated, not everything. A German doctor starts treatment only when confident of the diagnosis and the stage, so a pathologist re-examines the slides and blocks, and outdated or incomplete scans are done again. Sometimes this confirms the diagnosis made at home; sometimes it refines the stage or the tumour type, and then the whole treatment plan changes.
Can a patient in a serious condition travel for treatment?
Yes, but the decision is made from the records before the trip. The department assesses how it can help in that situation and whether the patient can manage the journey; if a regular flight is impossible, a flight with medical escort is arranged. The doctors say plainly what the goal of treatment is — cure, control of the disease or relief of symptoms — and sometimes that the trip would not help.
What happens after returning home?
At home the patient continues follow-up under the plan received at discharge. The discharge report states which tests and scans are due and when, which signs to watch for and when an in-person examination is needed. Check-up results can be sent to the treating doctor in Germany, who compares them with earlier ones and says whether anything should change; continuing drug treatment at home is agreed in advance with a local oncologist.
How AlenMed arranges treatment
AlenMed works with 86 partner hospitals in 38 German cities and with 345 doctors; the company office is in Munich. The hospital is chosen from the diagnosis, not from the loudness of a name: the patient’s records become a request to the department that treats exactly this kind of tumour and, where useful, to several hospitals so that their replies can be compared.
The company translates the medical records, books appointments, arranges the visa invitation, meets the patient on arrival and provides a medical interpreter at consultations. When the patient’s condition is serious, it arranges a flight with medical escort. The invoice comes from the clinic itself, and payment goes directly to it.
This material is for information only and does not replace a consultation with a doctor. Whether treatment is possible, what it will involve and what it will achieve can be determined only after an examination at the clinic in person.
Cancer types

News on this topic
Charité treats first beta-thalassemia patient with CRISPR
At Berlin Charité, a 19-year-old beta-thalassemia patient became the first in Germany to receive the newly approved CRISPR gene therapy Exagamglogene Autotemcel.
Real-World Breast Cancer Study Confirms High Five-Year Survival Rates in Germany
A landmark study of over 43,000 German patients reveals a five-year invasive disease-free survival rate of 82.9 percent in early hormone receptor-positive breast cancer.
FDA Approves Jülich Diagnostic Radiotracer FET for Brain Tumor Imaging
The FDA approves the diagnostic radiotracer FET (Pixclara®) for evaluating brain gliomas, highlighting decades of neuro-oncology research at Forschungszentrum Jülich.