EN
Prostate cancer often grows slowly and not every tumour needs treatment straight away, so the first question is not how to treat it at any cost but whether to intervene now, and how actively. Prostate cancer treatment in Germany follows this logic: as much treatment as is needed and not a step more.
This page explains how the diagnosis is confirmed, what the options are and who decides; for oncology care in general, see cancer treatment in Germany.
Prostate cancer in Germany: what patients arrive with
Patients seeking help with prostate cancer in Germany usually arrive with a raised PSA level or a diagnosis made at home. Age is the main risk factor, and most cases occur in men over seventy. In Germany men are offered an annual prostate examination from the age of 45 as part of the early detection programme. Early prostate cancer usually causes no symptoms, which is why it is found through PSA tests and examination.
A raised PSA is a reason to investigate, not a verdict. The German guideline now calls for an MRI of the prostate before the biopsy, so that tissue is taken from the suspicious areas rather than by needling the gland blind. This is called a fusion biopsy: during sampling, the MRI image is overlaid on the ultrasound image to guide the needle. The tests are described under prostate cancer diagnostics in Germany.
From the tissue the pathologist judges how aggressive the tumour is: the more the cells differ from normal tissue under the microscope, the higher the Gleason score. It is now translated into an ISUP grade group from 1 to 5: grade group 1 is a Gleason score of 6 or less and usually means a slow-growing tumour, grade group 5 the most aggressive form. This grading, not the diagnosis itself, decides what happens next: under the German S3 guideline on prostate cancer, a quiet tumour and an aggressive one are managed in completely different ways.
Active surveillance: when treatment can wait
Treatment can wait when the tumour is small, confined to the prostate and of low risk: it is then closely watched rather than treated at once, which is called active surveillance. For tumours in the lowest grade group the German guideline recommends it as the first step, and it can also be offered for some favourable tumours of the next group. The schedule includes regular PSA tests, a repeat MRI and a confirmatory biopsy; if the tumour moves up a grade or grows beyond the gland, surveillance ends and treatment is offered.
This is not “no treatment” but a deliberate decision of the tumour board, the joint meeting of specialists. In prostate cancer the risk lies not only in doing too little but also in doing too much: treating a tumour that would never have threatened a man’s life can leave him with incontinence or erection problems he did not need to live with. A rising PSA alone calls for a new MRI and biopsy, not automatically for surgery.
Surgery and radiotherapy
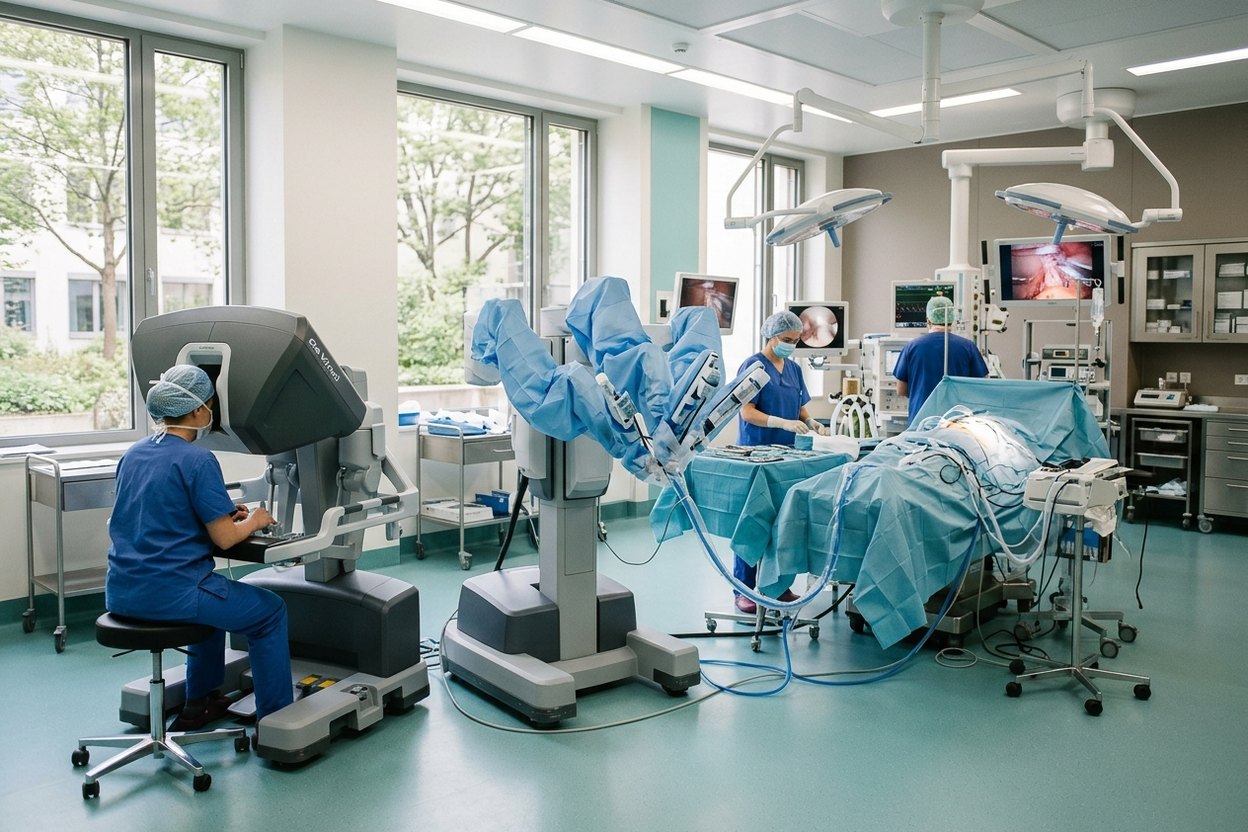
Most men who come for treatment in Germany for prostate cancer confined to the gland choose between two standard options aimed at a cure: removal of the prostate (radical prostatectomy) and radiotherapy. German hospitals increasingly operate with a surgical robot, through small incisions and with fine instruments that help spare the nerves responsible for continence and potency, though the surgeon’s experience matters as much as the robot. Urology at Munich Hospital Bogenhausen, for example, is headed by PD Dr. Atiqullah Aziz, who also leads its prostate cancer centre. At Essen University Hospital the urology clinic is directed by Prof. Boris Hadaschik, head of its uro-oncology centre. At the Agaplesion Frankfurt Diakonie Hospital, Prof. Georg Bartsch is chief physician of urology and heads the interdisciplinary centre for robot-assisted surgery. A mark of a specialised department is certification by the German Cancer Society (DKG), with regular outside audits of case volume, quality and organisation of care: among AlenMed’s partners, the Urology Clinic Munich-Planegg is certified for prostate cancer, and the Comprehensive Cancer Center Munich LMU includes a prostate centre.
Radiotherapy is the equal alternative: external beam radiotherapy is given from outside in a series of short sessions, while in brachytherapy the radiation source sits inside the prostate. Proton therapy is used only in selected cases, as it has not shown a clear advantage over modern conventional radiotherapy for this cancer. Radiotherapy is often preferred by older men and those for whom other illnesses make surgery riskier; for higher-risk tumours it is combined with hormone therapy for a limited period.
The tumour board weighs the tumour’s grade and stage, the man’s age, his other illnesses and his own priorities. Families often ask about the “best prostate cancer treatment in Germany”: honestly, there is no single best method, only the one that fits this man. Another frequent question is “is there a prostate cancer cure in Germany?”: early disease confined to the gland is often treated with curative intent, aiming to remove or destroy the whole tumour, but no clinic can guarantee an outcome. Each option has after-effects to discuss beforehand: after surgery, incontinence and erection problems are possible; after radiotherapy, irritation of the rectum and bladder; hormone therapy can bring hot flushes, fatigue and loss of bone density.
Focal therapy: treating only the tumour area
Focal therapy treats only the part of the prostate that holds the tumour, not the whole gland. Focused ultrasound (HIFU) heats the tissue, irreversible electroporation (NanoKnife) destroys cells with electrical pulses, cryoablation freezes the tissue, and photodynamic therapy uses a drug activated by laser light. It is discussed for a small tumour confined to one area and clearly visible on MRI.
In the current German S3 guideline these methods are not standard treatment. The guideline allows focal therapy only for a low-risk tumour on one side of the gland in men who decline both standard treatment and active surveillance; for intermediate-risk tumours it considers the data insufficient, and less-studied variants are for clinical trials only. Long-term results are far scarcer than for surgery and radiotherapy, and equal effectiveness has not been shown. Private clinics advertise these methods heavily to foreign patients: before paying, ask whether a tumour board discussed the case and how follow-up will work, with PSA tests, a control MRI and a check biopsy.
When the disease has spread beyond the gland
Once prostate cancer has spread beyond the gland, treatment works through the whole body: hormone therapy deprives the tumour of testosterone, often with newer hormone drugs, plus chemotherapy in aggressive disease. When patients ask about new prostate cancer treatment in Germany, they usually mean those newer drugs, PSMA-based imaging and radioligand therapy. PSMA-PET uses a weakly radioactive tracer that attaches to a protein on prostate cancer cells and reveals deposits invisible on ordinary scans; it is used when the risk of spread is high or PSA rises after treatment. For metastatic cancer that no longer responds to hormone therapy, radioligand therapy with lutetium-177 PSMA finds tumour cells by the same marker and irradiates them from inside. Immune drugs help in prostate cancer only when the tumour has certain molecular features, and “vaccine” courses at private clinics are not standard care.
At this stage the aim becomes control of the disease and quality of life rather than removal of the tumour. Treatments follow one another as the tumour responds, with bone-protecting medicines, pain relief and psychological support; more on this under advanced prostate cancer treatment.
Frequently asked questions
Which country has the best prostate cancer treatment?
No country is best for every man; what counts is a centre with the whole chain, from quality MRI and fusion biopsy to a tumour board, surgery and radiotherapy. German centres certified by the German Cancer Society are audited on exactly this. Compare the plan you are offered, not the flag on the building.
What is the best treatment for prostate cancer with the least side effects?
For a low-risk tumour, active surveillance usually means the fewest side effects, because nothing is done to the gland unless the tumour changes. Active treatment always has some: surgery mainly affects continence and erections, radiotherapy can irritate the bladder and rectum, and focal therapy may cause fewer problems but has less long-term evidence.
What is the most effective way to treat prostate cancer?
For a tumour confined to the prostate, surgery and radiotherapy have controlled the cancer equally well in randomised studies, so neither is more effective in general. What makes one of them the better choice is the tumour’s grade and stage and the man’s age and health.
What is the newest drug for prostate cancer?
There is no single newest drug: recent options in Germany include radioligand therapy with lutetium-177 PSMA, newer hormone tablets such as enzalutamide, apalutamide and darolutamide, and targeted tablets for tumours with changes in repair genes such as BRCA. They are used mainly once the disease has spread, depending on earlier treatment.
How AlenMed arranges treatment
To prepare a request, AlenMed needs the PSA results over time, the MRI images and the biopsy slides with the pathology report. The company works with 86 partner hospitals in 38 cities and 345 doctors; its office is in Munich. The records go to a urology department or uro-oncology centre, and the estimate comes from the clinic in the patient’s name, with prices explained under prostate cancer treatment cost. How soon treatment can start depends mainly on how complete the records are and whether tests must be repeated on site; the clinic sets exact dates after reviewing them.
AlenMed then handles translation of medical records, appointments, the visa invitation and an interpreter. A second opinion matters especially in prostate cancer, because it guards against both under- and over-treatment: a German specialist reviews the PSA history, images and slides and says plainly whether the proposed treatment is justified or a calmer route is possible.
This material is for information only, is not an offer and does not replace a consultation with a doctor. Whether treatment is possible, what it will involve and what it will achieve can be determined only by a doctor after an examination at the clinic in person.
News on this topic
Charité treats first beta-thalassemia patient with CRISPR
At Berlin Charité, a 19-year-old beta-thalassemia patient became the first in Germany to receive the newly approved CRISPR gene therapy Exagamglogene Autotemcel.
Real-World Breast Cancer Study Confirms High Five-Year Survival Rates in Germany
A landmark study of over 43,000 German patients reveals a five-year invasive disease-free survival rate of 82.9 percent in early hormone receptor-positive breast cancer.
FDA Approves Jülich Diagnostic Radiotracer FET for Brain Tumor Imaging
The FDA approves the diagnostic radiotracer FET (Pixclara®) for evaluating brain gliomas, highlighting decades of neuro-oncology research at Forschungszentrum Jülich.