EN
In Germany, colon cancer is treated with surgery and, where needed, drugs. Bowel cancer is treacherous because it keeps quiet for a long time. Mild discomfort in the abdomen, a change in the bowels, unexplained tiredness — all of that is easily put down to anything at all, and so the diagnosis often comes later than one would wish. German oncology relies here on two things: early detection while there are still no symptoms, and a precise understanding of the tumour once the diagnosis has been made.
This page covers the colon. Colon cancer treatment in Germany and the treatment of rectal cancer are planned differently, since the rectum, deep in the pelvis, is often irradiated before surgery; see rectal cancer treatment. In Britain it is called bowel cancer, so this is also about bowel cancer treatment in Germany.
Where the tumour sits and why it matters
The tumour’s position shapes the operation and, in part, the choice of drugs. The colon begins low on the right as the caecum and runs on as the ascending, transverse, descending and sigmoid colon; the rectum after it stands apart.
The right and left halves develop from different parts of the embryonic gut, and their tumours differ in biology. Right-sided tumours more often bleed unnoticed, causing anaemia and tiredness; left-sided ones change the bowel habit and cause cramping pain or visible blood. The side also guides the choice of targeted drugs in advanced disease.
Where does colon cancer come from? Risk rises with age, and most tumours grow over years from adenomatous polyps, benign growths of the bowel lining. Chronic inflammatory bowel disease and bowel cancer in close relatives add to the risk. In the hereditary forms, Lynch syndrome and familial adenomatous polyposis, follow-up and sometimes the extent of surgery change, and relatives are offered genetic counselling; the tumour’s MSI test helps flag Lynch syndrome.
Confirming the diagnosis
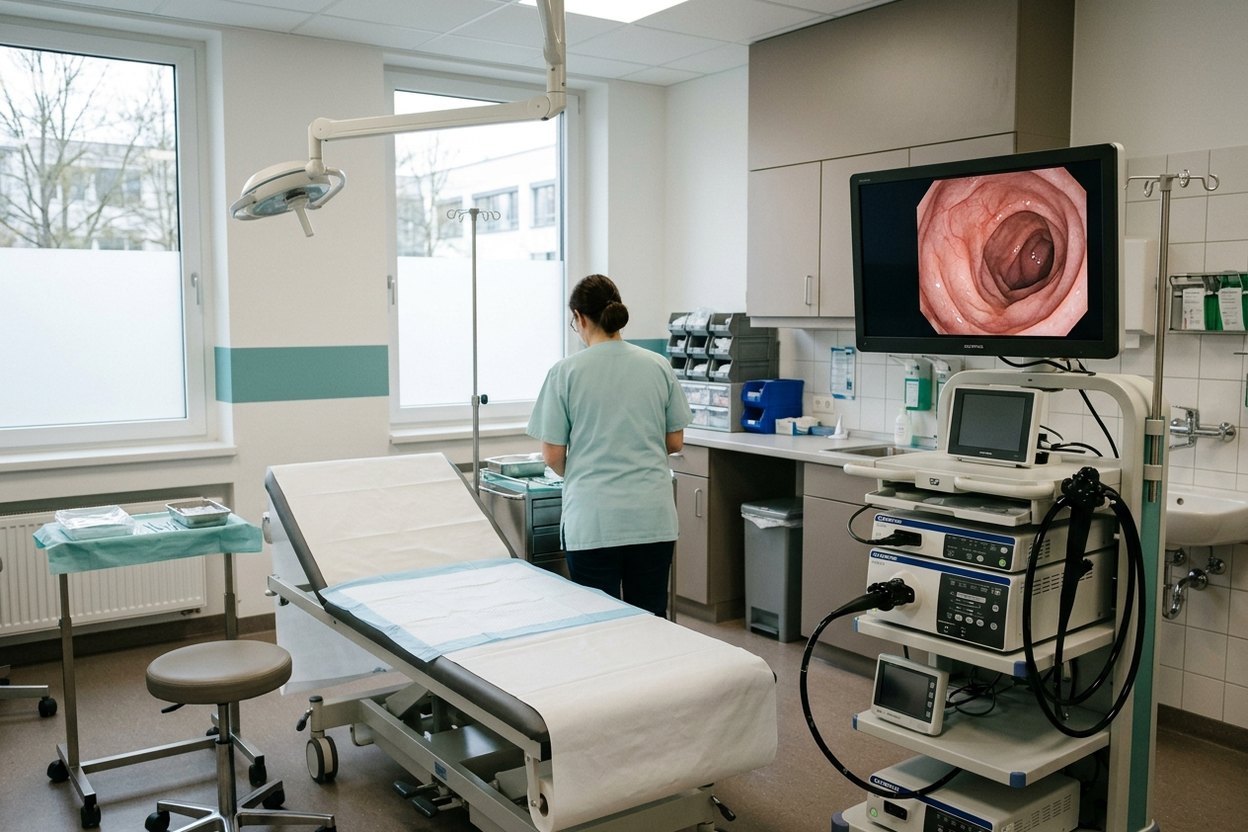
The main method is colonoscopy with biopsy: the doctor examines the bowel from inside and takes a piece of tissue for analysis. The whole colon is examined, because a second tumour can be present and missed at surgery.
Staging answers whether the disease has grown through the bowel wall and reached lymph nodes or other organs. It relies on CT of the chest, abdomen and pelvis, with MRI or contrast ultrasound for unclear liver spots. The CEA tumour marker is measured before treatment as a baseline.
As with other tumours, the tissue is studied beyond the microscope, since some medicines work only with particular tumour features. German guidelines call for testing every tumour for microsatellite instability (MSI), a fault in DNA repair that matters for stage II chemotherapy and immunotherapy. In advanced disease, a RAS mutation rules out one group of targeted drugs, while a particular BRAF mutation opens a dedicated combination. That step removes blind treatment.
Surgery
Surgery is the basis of treatment: the affected segment is removed with its blood supply and lymph nodes, and the ends of the bowel are joined. Tumours of the caecum or ascending colon mean removing the right half of the colon, those of the descending colon the left half (hemicolectomy); transverse and sigmoid tumours often need only a segment removed (resection). And plainly: a permanent stoma, the commonest fear, is very rarely needed.
Increasingly this is done gently — laparoscopically, through small ports, which means less pain and faster recovery, with the same cancer control as open surgery. German guidelines regard robotic assistance as equivalent to laparoscopy.
A good operation removes enough lymph nodes for honest staging and is done in a unit where such surgery is routine. The decision is made by a board, not by one surgeon: surgeon, oncologist, gastroenterologist, radiologist and pathologist decide together.
Drug therapy and stages
Chemotherapy after surgery depends on the stage and tissue analysis, not a template: none at stage I, at stage II only with risk factors and not for MSI tumours, and recommended at stage III, when lymph nodes are involved, to lower the risk of relapse. A course lasts several months; the Krebsinformationsdienst of the German Cancer Research Centre explains this in German.
In advanced disease, chemotherapy is combined with targeted drugs chosen by the RAS and BRAF results: EGFR antibodies for left-sided tumours with unchanged RAS, otherwise a drug blocking tumour blood vessel growth, and a dedicated combination for a particular BRAF mutation. MSI-H tumours (high MSI) are easy for the immune system to “see”, so immunotherapy comes first; see immunotherapy for bowel cancer.
The liver is the commonest site of spread, but liver metastases are not hopeless: a few can be removed, sometimes after drugs have shrunk them, and small ones destroyed with heat through a thin probe. If all tumour tissue is removed, a cure remains possible. For many metastases, see stage 4 colorectal cancer.
Choosing among the best German cancer clinics
What actually distinguishes German clinics in this diagnosis is a certified bowel cancer centre, the practical mark of the best German cancer clinics. A bowel cancer centre certified by the German Cancer Society (DKG) passes an external audit of case volume and quality every year, treats many patients, holds a weekly tumour board and has pathology that can be reviewed. Examples are the bowel cancer centres (Darmkrebszentrum) at Rotkreuzklinikum München and München Klinik Bogenhausen. In Berlin, the bowel cancer centre of DRK Kliniken Berlin is led by Prof. Gero Puhl. AlenMed checks each centre’s certificate when matching; see cancer hospitals in Germany.
Bowel cancer is one of the few that can be prevented: colonoscopy finds and removes on the spot the polyps from which a tumour might grow years later. That is why check-up programmes for people over fifty matter so much. A faecal occult blood test can come first, but a positive one leads to colonoscopy; see colonoscopy in Germany. A second opinion from a German specialist, based on your images, slides and letters, shows whether the stage and plan are right.
Frequently asked questions
Can colon cancer be cured?
At early stages, yes: a cure is possible, and much depends on whether the tumour was removed completely. While the disease is confined to the bowel and nearby lymph nodes, treatment aims at a cure. With distant metastases the aim is usually long control, although removable liver metastases still leave a chance of cure.
Will I need a stoma after the operation?
Very rarely in colon cancer: the surgeon joins the ends of the bowel, and stools pass the natural way. A temporary stoma is sometimes needed when the tumour has blocked the bowel or a join has leaked, and it is usually closed later. Permanent stomas mainly concern rectal cancer close to the sphincter.
Which records are needed for a review in Germany?
You will need colonoscopy and pathology reports, CT or MRI images in original digital format with reports, recent blood tests including CEA, letters on any treatment so far and, if done, MSI, RAS or BRAF results. Once translated, these let German doctors assess the case before any travel.
How AlenMed arranges treatment
AlenMed starts with a remote review of the records and matches the patient to a hospital with the right cancer centre. The hospital prepares a cost estimate, explained under treatment costs, and AlenMed helps with the visa invitation, the timing and an interpreter.
After discharge, the patient goes home with a follow-up plan for CEA tests, CT scans and colonoscopy, and AlenMed keeps a line of contact with the hospital open.
This material is for information only and does not replace a consultation with a doctor. Whether treatment is possible, what it will involve and what it will achieve can be determined only after an examination at the clinic in person. This page is not an offer.
News on this topic
Charité treats first beta-thalassemia patient with CRISPR
At Berlin Charité, a 19-year-old beta-thalassemia patient became the first in Germany to receive the newly approved CRISPR gene therapy Exagamglogene Autotemcel.
Real-World Breast Cancer Study Confirms High Five-Year Survival Rates in Germany
A landmark study of over 43,000 German patients reveals a five-year invasive disease-free survival rate of 82.9 percent in early hormone receptor-positive breast cancer.
FDA Approves Jülich Diagnostic Radiotracer FET for Brain Tumor Imaging
The FDA approves the diagnostic radiotracer FET (Pixclara®) for evaluating brain gliomas, highlighting decades of neuro-oncology research at Forschungszentrum Jülich.