EN
Bone cancer treatment in Germany starts not with choosing a method but with naming the tumour exactly: everything else depends on it. The tumours in question are sarcomas, tumours of connective tissue, here of the bone itself or the tissue around it. Their rarity makes the beginning hardest: not every doctor sees them often, and people often go through several consulting rooms before they hear a clear diagnosis.
Two situations need separating at once. A primary tumour grows in the bone itself; bone metastases come from a cancer of another organ, such as the breast or prostate. In adults, metastases are far more common and are treated quite differently, as part of the original cancer’s treatment (see cancer treatment in Germany). This page is about primary tumours.
The tumours that grow in bone
Primary bone tumours are not one disease: osteosarcoma, Ewing sarcoma and chondrosarcoma behave differently, occur at different ages and need different treatment. Osteosarcoma mostly affects teenagers and young adults, usually near the knee or in the upper arm, and osteosarcoma treatment in Germany combines chemotherapy with surgery. Ewing sarcoma also strikes the young, often in the pelvis, thigh or a rib, and responds to radiotherapy. Chondrosarcoma mostly affects adults, grows more slowly and responds poorly to drugs, so surgery carries its treatment.
The stage is not a single number. Doctors weigh the tumour’s size, whether it has grown beyond the bone or reached nearby vessels and nerves, and whether there are deposits elsewhere, above all in the lungs. This decides where treatment begins and whether the limb can be kept.
Not every lesion in a bone is cancer. The same images can show benign or intermediate tumours: giant cell tumour, aggressive but rarely spreading; osteochondroma, a cartilage-capped bony outgrowth; fibrous dysplasia, where bone is replaced by fibrous tissue. Some need no treatment at all, which is why nothing starts before histology, the examination of tissue under a microscope, confirms the diagnosis.
How the diagnosis is confirmed
Diagnosis moves from complaints to imaging, biopsy and tissue analysis. Warning signs are persistent bone pain unrelated to exertion and often felt at night, swelling over the bone, a stiffer nearby joint, or a fracture after a trivial injury; Ewing sarcoma may add fever and tiredness. In active, growing teenagers they are long blamed on a knock, sport or growing pains, but persistent bone pain needs an X-ray. Usually no cause is found; known risk factors are earlier radiotherapy to the area, Paget’s disease of bone in older people and rare inherited syndromes. Injury is not a proven cause, though it often prompts the first X-ray.
An X-ray is usually first to show a change in the bone. MRI then shows the tumour and its borders in soft tissue, chest CT looks for lung deposits, and bone scintigraphy or PET-CT checks the rest of the skeleton, alongside blood tests. But the decisive word belongs to the biopsy.
In bone tumours the biopsy is entrusted to the team that will later operate, and that is no formality. The biopsy track is removed together with the tumour at the operation, and a badly placed entry point can make limb-sparing surgery harder, so “just getting a sample locally” can close the door to keeping the limb. More on the procedure: biopsy in Germany.
In Germany a reference pathologist experienced in sarcomas reviews the tissue of rare tumours. Molecular testing, such as the search for the gene rearrangement typical of Ewing sarcoma, turns a probable diagnosis into a confirmed one. The US National Cancer Institute offers an overview of primary bone cancer.
What osteosarcoma treatment in Germany consists of
Osteosarcoma treatment in Germany consists of chemotherapy and surgery in a set order: chemotherapy first, then the operation, then further drug treatment. Ewing sarcoma follows the same order, while in chondrosarcoma surgery carries the main role. Chemotherapy before surgery shrinks the tumour and reaches microscopic deposits, and how well the tumour responded guides the rest of the plan.
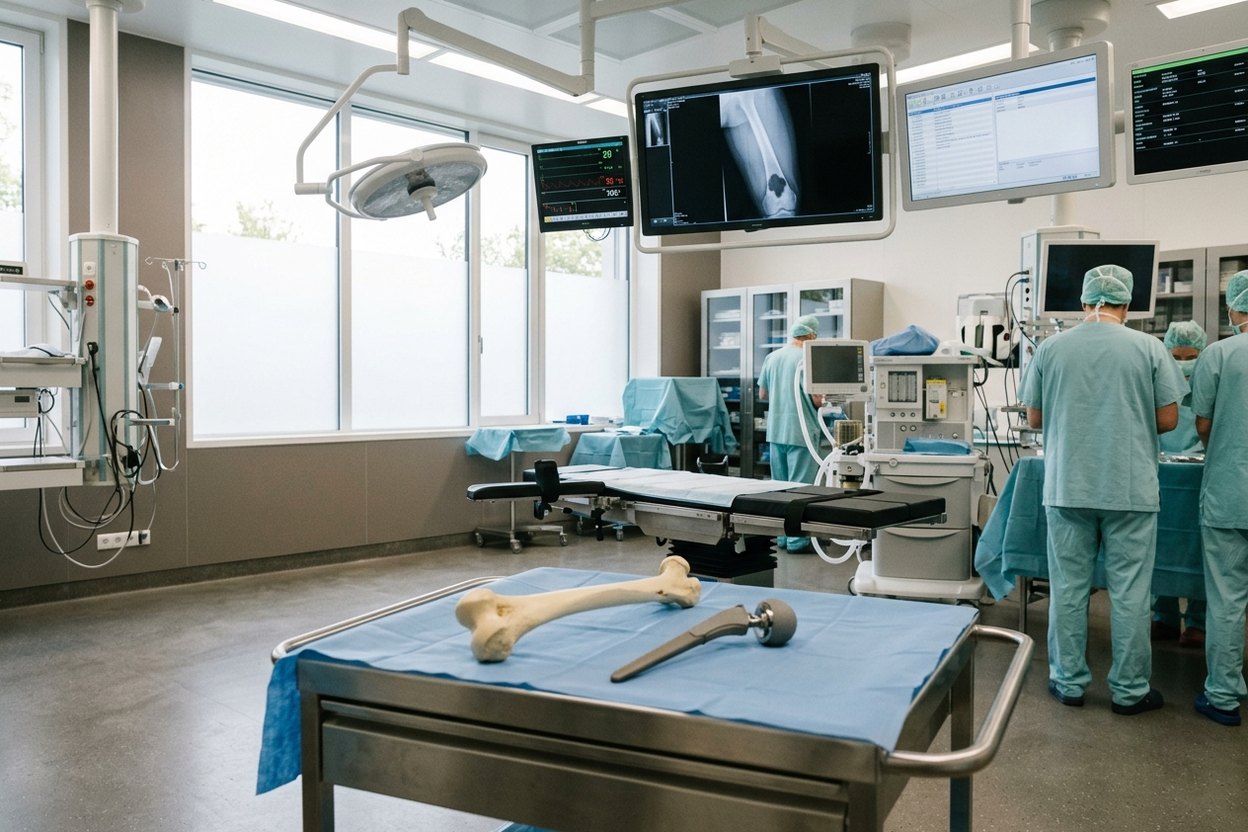
Limb-sparing surgery is the norm: the affected section of bone is replaced with a modular implant built to length, a bone graft or, in a growing child, an extendable prosthesis. Reconstruction can restore support and movement even after a large piece of bone is removed. Amputation is a last resort, though nobody can promise in advance to save the limb.
Radiotherapy is used selectively, above all in Ewing sarcoma and where surgery is difficult. Tumours near the spine or skull base may receive proton therapy, which better spares neighbouring structures; the tumour board decides on it, not testimonials. New drugs for a relapse are given within clinical trials, not as standard care: the sarcoma centre knows which trials are open and whether the patient qualifies.
Rehabilitation starts in hospital, where a physiotherapist teaches the patient to load the leg or arm with the implant, and often continues in a rehabilitation clinic (see cancer rehabilitation in Germany). Follow-up lasts for years: imaging of the operated site and the lungs, implant checks, lengthening of an extendable prosthesis in a growing child and, after chemotherapy, heart, hearing and kidney checks. The centre sets the intervals.
Where sarcomas are treated in Germany
Sarcomas belong in a centre that treats them routinely, with an orthopaedic oncologist, sarcoma pathologists, radiotherapy and a regular sarcoma board where oncologist, orthopaedic surgeon, radiation oncologist and pathologist review each case together. The German Cancer Society (Deutsche Krebsgesellschaft) certifies cancer centres and has a separate certificate for sarcoma centres; certified centres appear in the OncoMap search. Ask about that, not about reputation.
Osteosarcoma and Ewing sarcoma in teenagers are managed by paediatric oncologists on their own protocols (see paediatric oncology in Germany). PD Dr Claudia Blattmann is medical director of paediatric oncology, haematology and immunology at Klinikum Stuttgart. Professor Alexander S. Spiro at the Altona Children’s Hospital in Hamburg heads the section for deformities and tumour orthopaedics, the surgery that rebuilds a child’s bone after a tumour is removed.
Because these tumours are rare, a second opinion is a sensible step, not a luxury. A German sarcoma specialist reviews the images and slides and says whether they agree with the diagnosis and the order of the steps, so that the first and most important attempt is not lost.
Frequently asked questions
Does bone cancer always mean amputation?
No. Limb-sparing surgery is the norm: the affected bone is removed and replaced with an implant or a graft. Amputation is chosen when the tumour cannot otherwise be removed with a safe margin of healthy tissue. Whether the limb can be kept is decided by the sarcoma centre’s surgeon, and nobody can promise it in advance.
Can bone cancer be cured?
Yes, cure is possible, but chances differ from person to person. They depend on the tumour type, whether there were lung deposits at diagnosis, whether the tumour could be removed completely and how well it responded to chemotherapy before surgery. The prognosis is discussed by the centre’s doctor once all findings are in.
How are bone metastases treated?
Bone metastases are treated as part of treating the cancer they came from. Radiotherapy relieves pain and lowers the risk of fracture, bone-strengthening drugs slow the damage, and a bone at risk of breaking can be stabilised surgically. Which steps are needed, and when, is decided by the oncologist treating the main disease.
How AlenMed arranges treatment
AlenMed collects and translates the documents without which no remote assessment is possible: medical reports, images on disc, and slides or paraffin blocks for reference pathology. It sends them to a sarcoma centre, obtains the official cost estimate (Kostenvoranschlag), prepares the visa invitation and provides a medical interpreter. With an aggressive tumour the clock runs in weeks, and the trip is planned accordingly. Treatment runs over months in stages (chemotherapy, surgery with an implant, sometimes radiotherapy), so the centre prices it stage by stage; see sarcoma treatment costs in Germany.
The patient goes home with a written plan of the steps, the operation report, the implant documents, the chemotherapy protocol for continuing at home and the follow-up intervals. Rehabilitation after such operations is booked in advance.
This material is for information only and does not replace a consultation with a doctor. Whether treatment is possible, what it will involve and what it will achieve can be determined only after an examination at the clinic in person. This material is not an offer.
News on this topic
Charité treats first beta-thalassemia patient with CRISPR
At Berlin Charité, a 19-year-old beta-thalassemia patient became the first in Germany to receive the newly approved CRISPR gene therapy Exagamglogene Autotemcel.
Real-World Breast Cancer Study Confirms High Five-Year Survival Rates in Germany
A landmark study of over 43,000 German patients reveals a five-year invasive disease-free survival rate of 82.9 percent in early hormone receptor-positive breast cancer.
FDA Approves Jülich Diagnostic Radiotracer FET for Brain Tumor Imaging
The FDA approves the diagnostic radiotracer FET (Pixclara®) for evaluating brain gliomas, highlighting decades of neuro-oncology research at Forschungszentrum Jülich.